
Conditions treated
Back Pain
Low back pain is one of the most common reasons Australians see a doctor, and most episodes settle within a few weeks. When pain persists, keeps returning or starts to affect your legs, Dr David Edis can help you understand the cause and the right treatment path — which, for the majority of patients, does not involve surgery.

Overview
What is back pain?
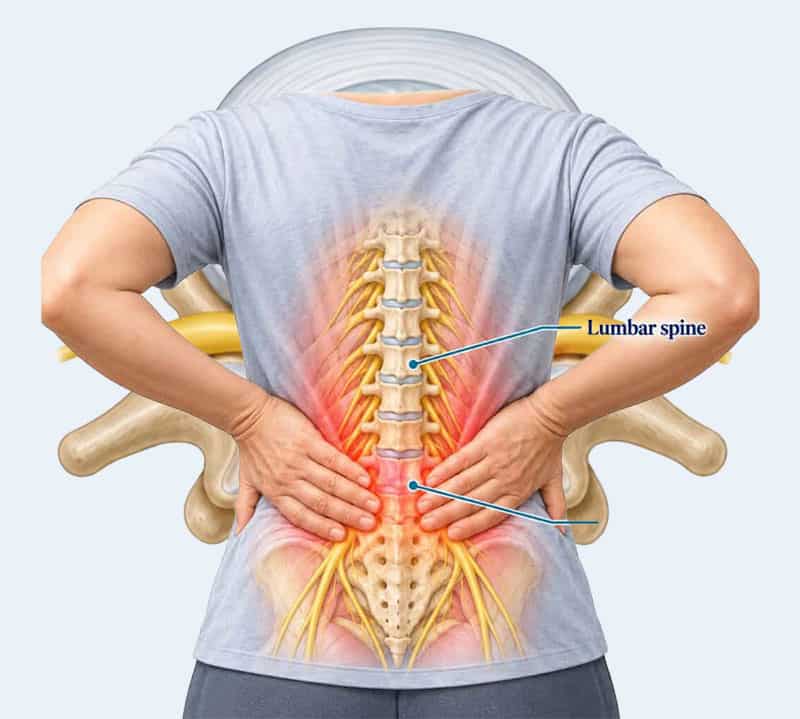
Back pain describes pain felt anywhere between the bottom of the rib cage and the top of the buttocks. It may be a dull ache, a sharp catching pain with movement, or stiffness that is worst first thing in the morning. It is usually “mechanical” — arising from the discs, facet joints, ligaments and muscles of the lumbar spine — rather than a sign of serious disease.
Back pain that also travels down the leg is usually a nerve problem and is covered on our sciatica and herniated disc pages.
Causes
What causes back pain?
In most cases no single structure can be blamed. Common contributors include disc degeneration and disc prolapse, wear in the facet joints, muscle and ligament strain, spondylolisthesis (a slipped vertebra) and, in older patients, spinal stenosis or osteoporotic fractures.
Less commonly back pain is caused by infection, tumour or inflammatory conditions. Warning signs that need prompt review include fever, unexplained weight loss, pain that is constant and worse at night, a history of cancer, or new bladder or bowel symptoms.
Timeframe
How long does it last?
Most episodes of acute low back pain improve substantially within two to six weeks, and around 90% of people are much better by three months. Staying active, continuing normal activities as far as pain allows and avoiding prolonged bed rest all speed recovery.
Pain lasting more than three months is described as chronic. It is still often mechanical, but at this stage a careful assessment to identify the pain source, and a structured rehabilitation program, are worthwhile.
Diagnosis
How is back pain diagnosed?
A thorough history and physical examination are the most important part of the assessment. Imaging is not needed for most short-lived episodes and can show age-related changes that are not the cause of pain. Dr Edis will arrange imaging when pain is persistent, when there are nerve symptoms, or when any of the warning signs above are present.
Plain X-ray
Not generally helpful for diagnosis on its own, but may give information that complements CT or MRI.
CT scan
Allows cross-sectional and multi-planar reconstructions so spine structures can be studied in detail. The disc prolapse can usually be seen.
MRI
The modality of choice for spinal disorders. Gives exquisite detail of nerves, discs and soft tissue, and uses no ionising radiation.
Bone scan
Nuclear medicine bone scans are sometimes used to supplement diagnosis in spinal disorders, but are typically not helpful in radiculopathy.
Treatment
Non-surgical treatment options.
The great majority of back pain is managed without surgery. Treatment focuses on controlling pain, restoring movement and building the strength and confidence to return to normal activity.
Stay active
Continuing to move, walk and carry out daily activities within the limits of pain leads to faster recovery than rest. Short periods of rest are fine in the first day or two, but prolonged bed rest slows healing.
Physiotherapy and exercise
A graded program of core strengthening, mobility and general conditioning is the most effective long-term treatment for recurrent and chronic back pain. Hands-on treatment can help in the short term.
Simple analgesics
Regular paracetamol and short courses of anti-inflammatory medication (NSAIDs) are the first-line options for pain control. Your GP can advise on what is safe for you.
Heat, massage and manipulation
These can provide useful short-term relief in an acute flare. They work best when combined with an active exercise program rather than used on their own.
Injections
Targeted injections — such as facet joint or nerve root injections — can help confirm the pain source and give temporary relief that allows rehabilitation to progress. They are not a long-term solution on their own.
Pain management and psychology
For persistent pain, a multidisciplinary approach involving pain specialists, physiotherapists and psychologists gives the best outcomes. Dr Edis works closely with these teams across south-east Melbourne and Gippsland.
Persistent pain
When is surgery considered?
Surgery is rarely needed for back pain alone. It is considered when a specific, correctable cause has been identified — such as a symptomatic disc prolapse, spinal stenosis or an unstable spondylolisthesis — and when a proper course of non-surgical treatment has not given adequate relief. Dr Edis will discuss with you honestly whether surgery is likely to help in your particular case.
Living with back or leg pain?
Dr David Edis and the team at Victorian Orthopaedic Spine Service will assess your symptoms, explain your diagnosis and recommend the treatment that best suits you.
Get in touch
Contact our rooms.
Our reception team will help you arrange a consultation, answer questions about your referral and let you know what to bring on the day.
Reception hours: Monday to Thursday 9am–4.30pm, Friday 9am–2pm
Response time: within 1–2 business days
Preparing for your appointment →
Referrals
A current GP or specialist referral is required.
Request a consultation
Send us your details and our reception team will be in touch. We aim to reply within 1–2 business days. Fields marked with an asterisk (*) are required.
All information is general in nature. Patients should consider their own personal circumstances and seek a second opinion. Any surgical or invasive procedure carries risks.